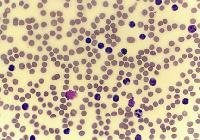
Chronic lymphocytic leukemia (chronic lymphoid leukemia, CLL) is a monoclonal disorder characterized by a progressive accumulation of functionally incompetent lymphocytes. It is the most common form of leukemia found in adults in Western countries.[1] Some patients die rapidly, within 2-3 years of diagnosis, because of complications from CLL, but most patients live 5-10 years.
Essential : FDA grants full approval to ofatumumab for use with chlorambucil in CLL
Ofatumumab (Arzerra) has been granted full approval by the FDA for use in combination with chlorambucil in previously untreated CLL patients who are not candidates for fludarabine-based therapy. The drug, a cytolytic monoclonal antibody, was approved by the FDA in 2009 for the treatment of CLL patients refractory to fludarabine and alemtuzumab.[2]
Full approval was based on result of a multicenter, randomized, open-label study of 447 patients who were not eligible for fludarabine-based therapy. Median progression-free survival was 22.4 months with combined ofatumumab and chlorambucil treatment vs. 13.1 months with chlorambucil monotherapy (hazard ratio, 0.57; stratified log-rank P value < .001).[2]
Signs and symptoms
Patients with chronic lymphocytic leukemia (chronic lymphoid leukemia, CLL) present with a wide range of symptoms and signs. Onset is insidious, and it is not unusual for CLL to be discovered incidentally after a blood cell count is performed for another reason; 25-50% of patients will be asymptomatic at time of presentation.
Symptoms include the following
Enlarged lymph nodes, liver, or spleen
Recurring infections
Loss of appetite or early satiety
Abnormal bruising (late-stage symptom)
Fatigue
Night sweats
See Clinical Presentation for more detail.
Diagnosis
Patients with CLL have a higher-than-normal white blood cell count, which is determined by complete blood count (CBC). Peripheral blood flow cytometry is the most valuable test to confirm a diagnosis of CLL. Other tests that may be helpful for diagnosis include bone marrow biopsy and ultrasonography of the liver and spleen. Immunoglobulin testing may be indicated for patients developing repeated infections.
Staging
There are 2 staging systems used for CLL.
The Rai-Sawitsky staging system categorizes patients into low-, intermediate-, and high-risk groups as follows:
Low risk (formerly stage 0) – Lymphocytosis in the blood and marrow only (25% of presenting population)[3]
Intermediate risk (formerly stages I and II) – Lymphocytosis with enlarged nodes in any site or splenomegaly or hepatomegaly (50% of presentation)
High risk (formerly stages III and IV) – Lymphocytosis with disease-related anemia (hemoglobin < 11 g/dL) or thrombocytopenia (platelets < 100 x 109/L) (25% of all patients)
The Binet staging system categorizes patients according to the number of lymph node groups involved, as follows:
Stage A – Hemoglobin greater than or equal to 10 g/dL, platelets greater than or equal to 100 × 109/L, and fewer than 3 lymph node areas involved.
Stage B – Hemoglobin and platelet levels as in stage A and 3 or more lymph node areas involved
Stage C – Hemoglobin less than 10 g/dL or platelets less than 100 × 109/L, or both
See Workup for more detail.
Management
Patients with early-stage CLL are not treated with chemotherapy until they become symptomatic or display evidence of rapid progression of disease. Early initiation of chemotherapy has failed to show benefit in CLL and may even increase mortality.
When chemotherapy is initiated, the nucleoside analogue fludarabine is the most commonly used first-line therapy in CLL. Combination regimens have shown improved response rates in several clinical trials and include the following:
Fludarabine, cyclophosphamide, and rituximab (FCR)[4, 5]
Pentostatin, cyclophosphamide, and rituximab (PCR)
Fludarabine, cyclophosphamide, and mitoxantrone (FCM)
Cyclophosphamide, vincristine, and prednisone (CVP)
Cyclophosphamide, doxorubicin, vincristine, and prednisone (CHOP)