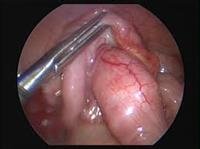
In children with appendicitis, laparoscopic appendectomy (LA) vs open appendectomy (OA) is linked to reduced risks for wound infection, abscess drainage, and duration of hospitalization, according to the results of a retrospective cohort study reported online June 20 in the Archives of Surgery.
"Since the adoption of ...LA for appendicitis, there has been continuing controversy over its benefits over ...OA," write Steven L. Lee, MD, from Harbor-UCLA Medical Center in Torrance, California, and colleagues. "In pediatric patients, the laparoscopic approach is still not considered standard of care because the recovery has been comparable with OA. Furthermore, there may be increased costs associated with LA."
The hypothesis tested by this study was that in children of all ages, LA and OA would have similar outcomes. Using discharge abstract data from 12 regional hospitals in Southern California, the investigators identified 7650 patients who underwent appendectomy for acute appendicitis via LA (n = 3551) or OA (n = 4099). The primary study endpoints were 30-day morbidity in wound infection, abscess drainage, readmission, and length of hospitalization.
In 1998, only 22% of appendectomies were done by LA, but this percentage increased to 70% in 2007. Compared with patients undergoing OA, those patients undergoing LA were older (mean age, 12.8 ± 3.2 years vs 10.4 ± 3.7 years; P < .001) and had a lower rate of perforation (24% vs 34%; P < .001).
For LA vs OA, the odds ratio (OR) was decreased for wound infection (OR, 0.6; 95% confidence interval [CI], 0.5 - 0.8) and abscess drainage (OR, 0.6; 95% CI, 0.4 - 0.7), based on multivariable logistic regression. Length of hospital stay was also shorter after LA vs OA, according to the results of multivariable linear regression.
"Now the preferred operation for children with appendicitis, LA was associated with a decreased risk of wound infection, abscess drainage, and length of hospitalization compared with OA," the study authors write. "...However, these findings were mainly seen in children older than 12 years."
Limitations of this study include retrospective review of a discharge database, inability to control for the different surgeons' preference for or experience with either technique, lack of randomization, potential for confounding, and lack of data regarding negative appendectomy rates and the duration of symptoms before presentation.
"Reflecting the influence of newly trained general and pediatric surgeons, almost all children, even those younger than 6 years, are currently treated with LA," the study authors conclude. "In addition, general surgeons appear to be more willing to perform LA in younger and smaller children. Despite the increasing performance of LA in younger children, it is still not certain whether the outcomes are superior to OA."